
When discussing hormonal health, conditions like irregular periods, stubborn weight gain, or acne are often treated as isolated reproductive issues. However, your metabolism and reproductive systems are intimately connected. At the center of this connection sits a powerful metabolic hormone: insulin.
When your cells stop responding to insulin effectively, a condition known as insulin resistance develops. Rather than remaining a simple blood sugar issue, insulin resistance triggers a metabolic domino effect that actively disrupts ovarian function, stops ovulation, disrupts the menstrual cycle, and forces the body to store fat instead of burning it. Understanding how this process begins is the key to breaking the cycle and regaining your natural rhythm.
How Insulin Resistance Starts: The Physiological Roots
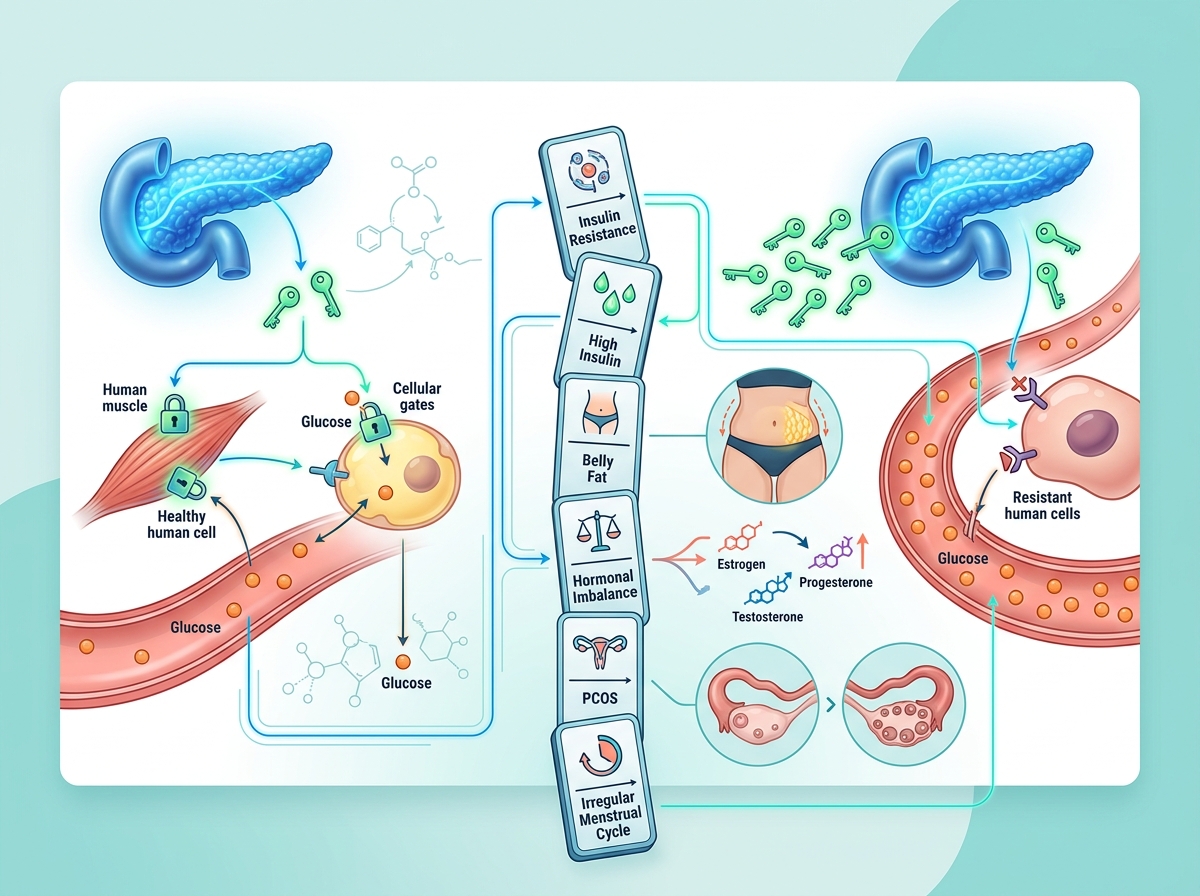
Every time you consume carbohydrates or sugars, your digestive system breaks them down into glucose, which enters your bloodstream. In response to rising blood glucose, your pancreas secretes insulin. Under healthy conditions, insulin acts as a chemical “key” that docks onto cell receptors (specifically in muscle, fat, and liver tissues), signaling them to absorb glucose from the blood to use for energy.
Insulin resistance begins when these cellular locks become desensitized. The progression typically follows these steps:
- Receptor Overload: Due to a chronic surplus of refined carbohydrates, processed sugars, systemic inflammation, or physical inactivity, blood glucose levels remain consistently high. The pancreas responds by pumping out massive amounts of insulin.
- Downregulation: Overwhelmed by the constant presence of high insulin, the cell receptors begin to “downregulate” or ignore the signal to protect themselves from glucose overload.
- Hyperinsulinemia: Because the cells refuse to let glucose in, blood sugar levels remain elevated. The pancreas overcompensates by pumping out even more insulin to force the glucose inside. This state of chronically elevated circulating insulin is called hyperinsulinemia.
Initial Symptoms of Insulin Resistance
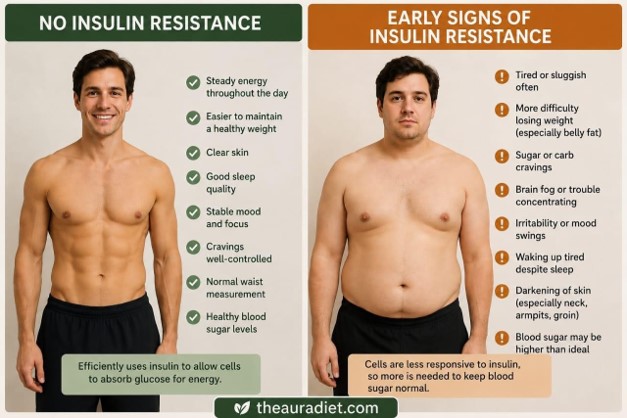
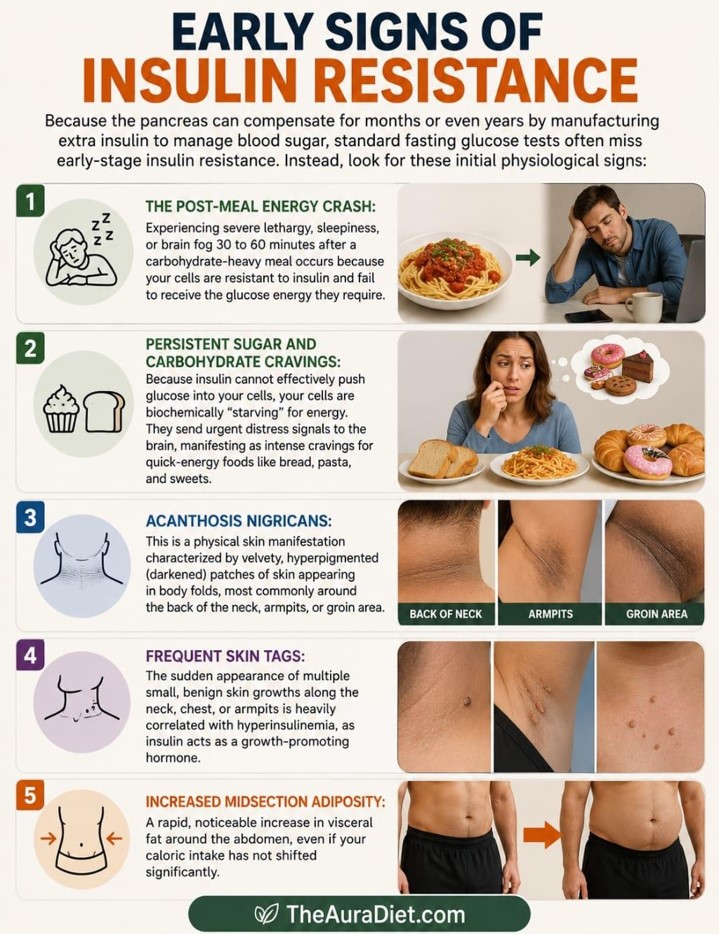
Post-Meal Energy Crash
Severe tiredness, sleepiness, or brain fog 30–60 minutes after carb-heavy meals because cells can’t take up glucose properly.
Intense Sugar & Carb Cravings
Cells are “starving” for energy, triggering relentless cravings for bread, pasta, pastries, and sweets.
Skin Changes
Dark, velvety patches called Acanthosis Nigricans in skin folds (neck, armpits) and the sudden emergence of skin tags.
Increased Visceral Belly Fat
Rapid accumulation of stubborn fat around the midsection and abdominal organs, even without increased calorie intake.
Additional clinical signs and metabolic markers are illustrated below:
The Weight Gain Trap: How Insulin Drives Fat Storage
Many individuals struggling with insulin resistance find themselves trapped in a frustrating cycle: they reduce calories and exercise more, yet the scale refuses to move. This is because insulin is not just a blood sugar regulator; insulin is your body’s primary fat-storage hormone.
1. Invalidation of the Lipolysis Process
Under normal conditions, when insulin levels drop (such as during overnight fasting or between meals), your body activates lipolysis—the breakdown of stored fat cells to burn for fuel.
2. Shunting Energy into Fat Cells
Because resistant muscle cells refuse to accept glucose, the liver is forced to clear excess sugar from the bloodstream. It converts this surplus glucose into triglycerides, which are then aggressively shunted directly into adipose tissue—predominantly around your abdominal organs (visceral fat).
3. Cellular Starvation and Decreased BMR
Because cells cannot access the circulating energy from food, the body downregulates metabolic burn to conserve fuel. This produces chronic fatigue, leaving you with less physical stamina to move while simultaneously suppressing your Basal Metabolic Rate (BMR).
How Insulin Resistance Disrupts Hormones and the Menstrual Cycle
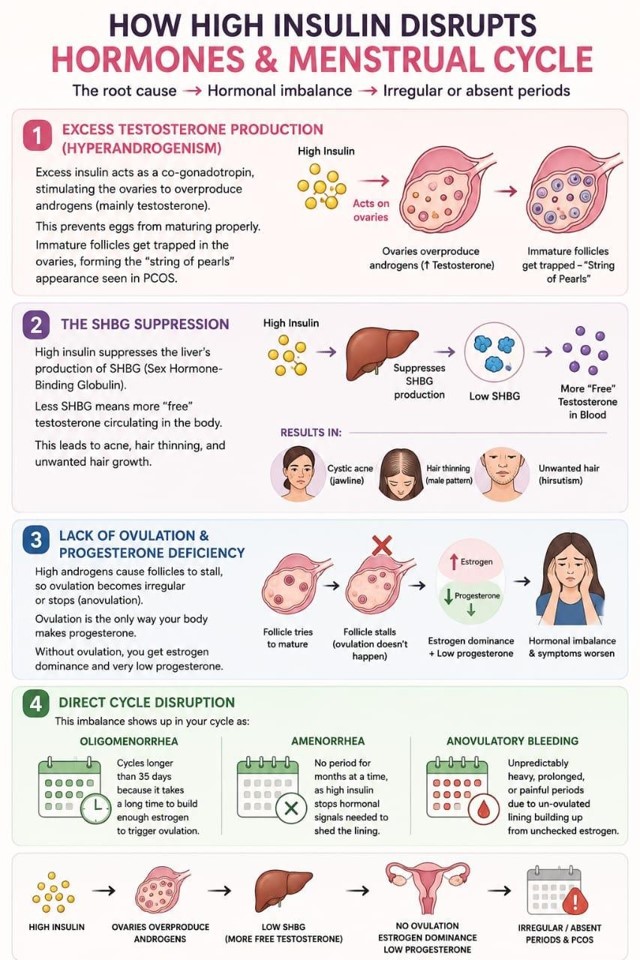
The ovaries are exquisitely sensitive to metabolic shifts. When system-wide insulin spikes, it upends the delicate balance of estrogen, progesterone, and androgens, leading to severe ovulatory dysfunction and cycle irregularity.

- Excess Testosterone Production: High insulin directly stimulates ovarian theca cells to overproduce androgens, arresting egg maturation and causing immature follicles to cluster in a classic “string of pearls” PCOS appearance.
- Lower SHBG Levels: Insulin suppresses liver production of Sex Hormone-Binding Globulin (SHBG), leaving more “free” testosterone unbound in the bloodstream to trigger jawline cystic acne, hirsutism, and androgenic hair thinning.
- No Ovulation, Low Progesterone: Stalled follicular growth means anovulation (no egg released). Without ovulation, the corpus luteum cannot form to produce progesterone, creating an unbalanced state of estrogen dominance.
- Irregular or Missing Periods: This endocrine block causes oligomenorrhea (cycles longer than 35 days) or full secondary amenorrhea (missing cycles for months).
- Anovulatory Bleeding: Without progesterone to stabilize the uterine lining, unchecked estrogen causes erratic endometrium buildup, resulting in unpredictably heavy, prolonged, or painful periods.
Reversing the Cycle: Natural Management
The endocrine and metabolic systems respond remarkably well to targeted lifestyle shifts. Cellular sensitivity to insulin can be restored through consistent daily interventions:
1. Adopt a Low-Glycemic, Protein-Forward Diet
Shift your nutrition away from refined carbohydrates and fast-acting sugars that provoke acute insulin surges. Prioritize clean proteins (eggs, wild fish, pasture-raised poultry) and viscous fibers (lentils, seeds, non-starchy greens). Pair these with anti-inflammatory fats (avocados, extra virgin olive oil), and practice food sequencing (fiber first) to blunt postprandial glucose curves.
2. Utilize Skeletal Muscle Dynamics
Skeletal muscle is your body’s primary clearinghouse for glucose. Resistance training or bodyweight strength work 3 to 4 times a week builds metabolically active tissue that clears blood sugar independently of insulin. Furt
Keep Reading
- Insulin Resistance and PCOS: Why Calorie Cutting Fails
- Food Sequencing for PCOS: The Science of Eating Fiber First
hermore, a 15-minute walk taken immediately following major meals utilizes non-insulin GLUT4 transporters, significantly reducing pancreatic workload.
3. Regulate Circadian Rhythms & Sleep
A single night of sleep deprivation elevates morning cortisol, instantly triggering acute insulin resistance the following day. Prioritizing 7 to 8 hours of uninterrupted, restorative sleep lowers nocturnal stress hormones and allows metabolic and reproductive tissues to repair.

D I E T . G L O W . R E P E A T





